Read the AI-Generated Article 100% AI-generated · not peer-reviewed · click to expand
Abstract
This article argues that paper’s persistence after digitization is not best explained as technological backwardness, nostalgia, or mere noncompliance. Frontline workers preserve or recreate paper when official digital systems fail four practical tests: speed at the point of action, trust and repairability, visibility of situationally relevant cues, and ergonomic fit with embodied work. Paper therefore operates as frontline infrastructure: a memory aid, temporary working surface, display device, repair buffer, and sometimes a shadow record. Its value is conditional. In some settings it supports safety, coordination, and professional judgment; in others it produces double entry, delayed official records, hidden administrative labor, opacity, and transcription-error risk.
The article develops this position through a cross-sector secondary analysis of reported evidence from health care, schools, warehouses, and public administration, while explicitly not claiming to have collected new field data or conducted a meta-analysis. It proposes a practitioner-oriented case-study application protocol centered on the “recordkeeping episode,” supported by an author-generated double-entry exposure heuristic, audit questions, and a decision matrix for governing paper after digital implementation. The analysis shows that digital records outperform paper when embedded in task flow, linked to immediate operational value, and designed for repairability and ergonomic use; conversely, paper returns when digital systems relocate work, hide relevant cues, or undermine trust. The article’s practical contribution is diagnostic: managers, clinicians, educators, warehouse supervisors, and public-service administrators should first ask what work paper is doing before deciding whether to redesign, formalize, replace, or prohibit it.
Introduction
Paper forms were supposed to recede as hospitals, schools, warehouses, and public offices adopted electronic records, data platforms, barcode systems, and automated case tools. Yet the empirical record assembled across these sectors shows a more durable pattern: paper often returns quietly, not as a nostalgic attachment to older office routines, but as a working infrastructure for remembering, coordinating, checking, repairing, and protecting professional judgment. In primary care clinics with integrated electronic health records, paper remained useful for memory, efficiency, and making clinical problems visible; clinicians and staff also used computer-based workarounds such as copying and pasting despite institutional prohibitions (Flanagan et al., 2013). In hospital nursing, EHR workarounds include omitted steps, out-of-sequence steps, and unauthorized steps, with paper notes and handwritten notes later transcribed into the EHR appearing as care-work tools rather than simple resistance to technology (Fraczkowski et al., 2020). In schools, even multiple commercial data systems can depend on extensive manual maintenance, spreadsheets, phone calls, printed documents, and handwritten inputs (Grant, 2024). In public administration, paper files have carried “meta-information” that workers judged essential to professional practice and authority (Komito, 1998).
The issue matters because paper’s return is not benign in all circumstances. Informal paper capture can help workers act quickly, but it can also create double entry, delayed official records, transcription-error risks, and invisible administrative labor. A systematic review of health information technology and nurses’ time found that nurses often documented informally on paper before entering the same information electronically, producing duplication and potential transcription-error risk; the same review also reported that EHR implementations increased nursing documentation time in weighted averages of +22% and +46%, while barcode medication administration reduced medication-administration time by 33% (P < .05) (Moore et al., 2020). Paper therefore cannot be read either as a failure of modernization or as a harmless supplement. It is a situated response to design, workload, trust, and accountability conditions.
Prior work has established several pieces of this puzzle. Health informatics studies document that paper persists inside mature EHR environments because it supports memory, visibility, safety, and workflow smoothing (Flanagan et al., 2013; Stevenson et al., 2016). Nursing research identifies usability barriers, environmental constraints, patient-specific barriers, insufficient time, barcode or ID accessibility problems, and multi-screen documentation requirements as causes of workarounds (Fraczkowski et al., 2020). Education research shows that datafication can move rather than remove recordkeeping labor, creating hidden infrastructural tasks such as data cleaning, cross-platform transfer, chasing late entries, and report production (Grant, 2024). Studies of warehouses show the counterpoint: when digital recording is embedded in actual task flow and provides immediate operational value, compliance can improve and workers may accept digital systems (Goomas & Yeow, 2013; Nair et al., 2018). Public-office studies show that electronic or automated representations still require interpretation, repair, and professional improvisation (Jørring, 2025; Komito, 1998).
The gap is not simply that paper has been understudied. The more consequential gap is that sector-specific studies have not fully translated into a practitioner framework for deciding when analog recordkeeping is a legitimate frontline cognitive aid, when it is a symptom of dangerous system misfit, and when it becomes a shadow bureaucracy that increases error and workload. A hospital manager, school data lead, warehouse safety supervisor, or public-service administrator needs more than the instruction to “go paperless” or “respect workarounds.” They need a way to diagnose paper’s function in the local task ecology.
This article defends the following thesis: frontline workers prefer or preserve paper when official digital systems fail four practical tests—speed at the point of action, trust in the record and its repairability, visibility of situationally relevant cues, and ergonomic fit with embodied work. Paper’s quiet return is therefore best understood as an adaptive response to system design and organizational accountability pressures, not as a stable preference for analog media. The argument proceeds by reframing paper as infrastructure, specifying a research design that practitioners could use to study paper’s return without pretending this article has collected new field data, presenting a secondary analysis of source-reported findings, examining mechanisms of trust, speed, errors, and hidden work, addressing the strongest counterarguments in favor of digital recordkeeping, and translating the evidence into an application protocol for practice.
From Residue to Infrastructure: What Paper Does at the Front Line
The phrase “paperless workplace” invites a misleading image: paper as a residue left behind by incomplete implementation. The studies considered here suggest a different interpretation. Paper can function as a local infrastructure: a set of material supports that workers use to make tasks doable under time pressure, uncertainty, fragmented systems, and accountability demands. This is an author-generated synthesis, but each element of it is grounded in documented uses of paper and parallel records across the cited sectors.
Paper as a cognitive and visual aid in clinical work
In clinical settings, paper’s persistence is closely tied to cognition and visibility. Flanagan et al. (2013) observed paper- and computer-based workarounds across 11 primary care clinics at three benchmark health IT institutions. The important point is not merely that paper survived inside advanced electronic environments. It is that paper remained useful for memory, efficiency, and making clinical problems visible. The authors explicitly resist a simple “paper equals failure” narrative, arguing that it is unrealistic to expect EHRs to eliminate all paper-based cognitive aids and that workaround patterns should inform human-factors redesign rather than simply be prohibited (Flanagan et al., 2013).
Vital-sign documentation provides a more acute version of the same dynamic. Stevenson et al. (2016) examined workflow processes in a 372-bed Swedish hospital and found paper workarounds including handwritten notes and eight pre-printed paper observation charts despite the presence of electronic records. Their interpretation matters for practitioners: nurses created paper workarounds to smooth workflow and support patient safety, while vital-sign documentation accuracy and completeness remained critical for recognizing patient deterioration (Stevenson et al., 2016). In this case, paper is neither merely redundant nor automatically safe. It is a temporary working surface for tasks where delay, incomplete capture, or poor visibility can matter clinically.
The integrative review by Fraczkowski et al. (2020) reinforces this interpretation by classifying nurses’ EHR workarounds into omitted process steps, steps performed out of sequence, and unauthorized process steps. Those categories are often treated as compliance problems. Yet the causes identified in the review—organizational factors, environmental constraints, patient-specific barriers, insufficient time, barcode and ID accessibility problems, and usability issues such as needing multiple screens to complete one action—show that the workaround often begins as an attempt to reconcile official process with situated care work (Fraczkowski et al., 2020). The presence of paper RN notes and handwritten notes later transcribed into the EHR in one included qualitative study supports the reading of paper as a care-work tool rather than merely a sign of technological refusal (Fraczkowski et al., 2020).
Paper as bureaucratic craft in schools and public offices
In schools, the persistence of paper and spreadsheets is tied less to bedside urgency and more to the maintenance of institutional data systems. Grant’s (2024) sociomaterial ethnography of a secondary school in England, conducted from the school’s data office across three periods in one school year, found that at least two commercial data-management platforms did not remove manual recordkeeping. Staff created a bespoke pupil performance and intervention system, processed six yearly “data drops,” chased late teacher entries, accounted for missing data, and used spreadsheets, phone calls, handwritten notes, printed documents, physical displays, and software outputs (Grant, 2024). A full-time administrator performed essential data entry, cleaning, pupil-record maintenance, handwritten-data input from teachers and parents, cross-platform transfer and translation, report compilation, and printing and circulating paperwork (Grant, 2024).
The school case is central because it shifts the analytical focus from “user adoption” to “infrastructural maintenance.” Where a digital system appears complete to senior leaders, frontline or back-office staff may be sustaining it through translation, reconciliation, and repair. The paper form is not outside the data system; it is one of the means by which the data system is made to function. That claim is an author’s interpretation of Grant’s (2024) evidence, but it follows directly from the documented dependence on handwritten inputs, printed circulation, cross-platform transfer, and data cleaning.
Komito’s (1998) ethnographic study of Lotus NOTES in an Irish civil-service unit handling disputes over benefit claims adds a further layer: paper files may carry perceived “meta-information” that the electronic file does not preserve. Workers treated the interpretive knowledge embedded in paper files as necessary professional expertise, and Komito also identifies a power and status dimension in which reliance on paper helped defend occupational authority (Komito, 1998). This finding complicates purely functional explanations. Paper may be useful because it is fast or visible, but it may also protect professional discretion in organizations where digital records standardize what counts as knowledge.
Paper after automation: representations still need repair
Automation does not eliminate this problem; it can shift it. Jørring’s (2025) study of Danish employment services, based on 25 interviews and more than 80 hours of observations, examines how frontline workers make automatically generated client representations usable and meaningful. The study identifies three digital coping strategies: automatic preparation, which simplifies; extended preparation, which complicates; and in situ preparation, which shifts work into the client meeting through flexible searching and professional improvisation (Jørring, 2025). This evidence matters because it shows that digital records do not automatically “prepare” frontline workers for interaction. Workers must repair, interpret, supplement, or strategically ignore system-produced representations (Jørring, 2025).
Across these settings, the recurring issue is not paper versus screen as a matter of preference. It is the gap between an official representation and a workable representation. A workable representation is one that can be used at the time, place, and pace of frontline action. That definition is an author-generated analytic term, not a quoted concept from the sources. It helps connect the observed clinical notes, school spreadsheets, warehouse scanners, paper case files, and automated client profiles without claiming that the sectors are identical.
Official digital record → may be complete for audit, billing, reporting, or compliance
Frontline working record → must be fast, visible, trusted, repairable, and ergonomically available
Paper returns when the distance between these two records becomes operationally costly.
A Case-Study Application Protocol for Diagnosing Paper’s Return
Because this article did not collect new field data, the case-study component is presented as a fully specified application protocol that a practitioner organization could execute. The design is intentionally cross-sectoral because the evidence base suggests that analog recordkeeping recurs in different institutional environments for related but not identical reasons. The protocol would compare one hospital unit, one school data process, one warehouse safety process, and one public-office casework process. These are not proposed as statistically representative sites. They are theoretically selected settings in which the cited literature has already documented the persistence or replacement of paper: clinical EHR workarounds (Flanagan et al., 2013; Fraczkowski et al., 2020; Stevenson et al., 2016), school data infrastructuring (Grant, 2024), IT-assisted warehouse safety checks (Goomas & Yeow, 2013), ergonomic scanner-mediated work (Nair et al., 2018), and bureaucratic or automated public-service recordkeeping (Jørring, 2025; Komito, 1998).
Unit of analysis: the recordkeeping episode
The proposed unit of analysis is the recordkeeping episode: a bounded sequence in which a frontline worker captures, consults, modifies, transcribes, verifies, or circulates information for an operational purpose. In a hospital, that episode could include taking vital signs on paper, entering them into the electronic record, and using the record to detect deterioration; Stevenson et al. (2016) show why vital-sign accuracy and completeness matter for recognition of deterioration. In a school, it could include a teacher’s entry during a data drop, the data office’s chase for missing information, and the administrator’s later cleaning and report compilation; Grant (2024) documents six yearly data drops and the surrounding maintenance work. In a warehouse, it could include a pre-shift equipment safety check, with either a pre-printed paper inspection report or a computerized check integrated into the warehouse management system and barcode readers; Goomas and Yeow (2013) provide a concrete example of this comparison. In public offices, it could include preparation for a client meeting using an automated profile and the worker’s in situ searching or supplementation; Jørring (2025) documents this kind of digital coping.
This episode-level focus avoids a common measurement error: counting whether an organization “has” a digital system rather than studying whether the digital system is usable at the point where the record is needed. The evidence justifies this distinction. Benchmark health IT institutions still contained paper and computer workarounds (Flanagan et al., 2013). A school with multiple commercial platforms still depended on hidden manual work (Grant, 2024). A distribution center’s computerized safety-check system succeeded not simply because it was digital, but because it blocked work assignment until checks were completed and gave immediate feedback (Goomas & Yeow, 2013).
Data sources the protocol would use
The proposed protocol would combine four forms of evidence. First, structured observations would follow recordkeeping episodes from first capture to official entry. This mirrors the observational strength of Flanagan et al. (2013), Stevenson et al. (2016), Grant (2024), and Jørring (2025), though this article has not replicated those observations. Second, artifact collection would catalogue paper forms, printed lists, handwritten notes, spreadsheets, scanner screens, system prompts, and reports. This is appropriate because the cited studies show that material artifacts carry important workflow functions: pre-printed observation charts in hospital vital-sign documentation (Stevenson et al., 2016), paper files in civil-service disputes (Komito, 1998), spreadsheets and printed paperwork in school data work (Grant, 2024), and barcode-mediated computerized checks in warehouses (Goomas & Yeow, 2013). Third, short worker interviews would ask what the analog or digital record lets them do, what it prevents, where they fear error, and which entries they do not trust. Fourth, administrative document review would identify policies that prohibit, tolerate, or depend on unofficial records; the relevance of policy is evident where copying and pasting continued despite institutional policy against it (Flanagan et al., 2013).
| Protocol element | What the practitioner would examine | Evidence base for including the element | Potential diagnostic question |
|---|---|---|---|
| Recordkeeping episode | Capture, consultation, correction, transcription, verification, and circulation of a record | Paper and computer workarounds were observed around EHR use and vital-sign documentation (Flanagan et al., 2013; Stevenson et al., 2016). | Where does the worker first write or enter the information, and where does the official record finally reside? |
| Material artifacts | Paper forms, notes, charts, spreadsheets, scanners, screens, printed reports | Studies document handwritten notes, pre-printed observation charts, paper files, spreadsheets, printed school documents, and barcode-based systems (Goomas & Yeow, 2013; Grant, 2024; Komito, 1998; Stevenson et al., 2016). | Which artifact is closest to the moment of action? |
| Trust and repair | Difficulty correcting, retrieving, or relying on data entered by others | Nurses reported EHR-related stressors including incomplete EHR work by other departments and difficulty correcting or retrieving data (AlQahtani et al., 2021). | Which record do workers treat as safest when the official record is incomplete or hard to correct? |
| Embodied fit | Scanning, carrying, screen navigation, wrist motion, barcode accessibility, multi-screen requirements | Nursing workarounds were linked to barcode/ID accessibility and multi-screen usability problems; warehouse scanner design is an ergonomic issue (Fraczkowski et al., 2020; Nair et al., 2018). | Does the recordkeeping device fit the body position, pace, and repetition of the work? |
| Double entry | Informal paper documentation followed by formal electronic entry | Nurses often documented informally on paper before entering the same information electronically, creating duplication and transcription-error risk (Moore et al., 2020). | How often must workers translate one record into another before the task is complete? |
The protocol would not begin by asking whether paper should be eliminated. It would classify the function of each analog record. The distinction matters because the evidence includes paper that supports safety and memory (Flanagan et al., 2013; Stevenson et al., 2016), paper that creates duplication and transcription risk (Moore et al., 2020), and digital systems that reduce missing forms when designed into the work process (Goomas & Yeow, 2013). A ban on paper would treat unlike cases as identical.
A simple heuristic for the protocol is the following author-generated measure. It is not an empirical result; it is a proposed way to structure local inquiry into duplication risk:
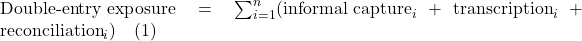
The heuristic reflects Moore et al.’s (2020) finding that informal paper documentation followed by EHR entry can create duplication and transcription-error risk. It also reflects Grant’s (2024) account of school data labor as cross-platform transfer, cleaning, handwritten-data input, and report compilation. Practitioners could operationalize each term locally by observing episodes and counting transitions between artifacts, but no such count is performed in this article.
Secondary Analysis of Reported Evidence: Speed, Safety, Stress, and Hidden Labor
The following secondary analysis uses only values reported in the cited sources. It does not pool the studies statistically because the designs, sectors, outcomes, and units of analysis differ. Instead, it aligns reported findings around the article’s four practical tests: speed, trust and repairability, visibility, and ergonomic fit. This kind of cross-case synthesis is interpretive rather than experimental.
| Sector or setting | Source-reported empirical basis | Reported value or finding | Relevance to the argument |
|---|---|---|---|
| Primary care clinics | Direct observations in 11 primary care clinics with integrated EHRs | Paper remained useful for memory, efficiency, and making clinical problems visible; copying and pasting occurred despite policy against it. | Paper and digital workarounds persist even in benchmark health IT settings (Flanagan et al., 2013). |
| Nursing EHR work | Integrative review of qualitative and quantitative studies | Workarounds grouped as omitted steps, out-of-sequence steps, and unauthorized steps; causes included organizational, environmental, patient-specific, time, barcode/ID, and usability barriers. | Analog workarounds respond to workflow constraints rather than only to attitudes toward technology (Fraczkowski et al., 2020). |
| Hospital vital signs | Qualitative observations and interviews in three clinical areas of a 372-bed Swedish hospital | Handwritten notes and eight pre-printed paper observation charts were used despite electronic records. | Paper can smooth workflow and support patient safety where documentation completeness matters (Stevenson et al., 2016). |
| Nurses’ time and HIT | PRISMA-based systematic review: 33 studies from 1,647 initial records | EHR implementations showed weighted documentation-time increases of +22% and +46%; BCMA reduced medication-administration time by 33% (P < .05). | Digital systems can either increase documentation burden or save time depending on task fit (Moore et al., 2020). |
| Nurses’ EHR stress | Survey of 212 nurses at a tertiary eye hospital in Saudi Arabia | 106 nurses, 50% of respondents (95% CI 43.3–56.7), reported EHR-related stress; 35 nurses, 16%, reported severe stress. | Trust, correction, retrieval, and interdepartmental dependencies shape digital record experience (AlQahtani et al., 2021). |
| School data systems | Sociomaterial ethnography of one secondary school in England | At least two commercial data-management platforms coexisted with a bespoke system, six yearly data drops, spreadsheets, phone calls, handwritten notes, printed documents, and full-time administrative data work. | Digitization redistributed recordkeeping into hidden infrastructural maintenance (Grant, 2024). |
| Special education administration | GAO review, nine focus groups with administrators and educators from 37 states, school visits, and stakeholder interviews | Educators commonly estimated spending roughly one to two hours per day on administrative tasks; no state applied for multi-year IEP pilots. | Documentation burden is real, but records also serve accountability, planning, and student-support functions (U.S. Government Accountability Office, 2016). |
| Warehouse safety checks | Case study comparing an eight-week paper baseline with a five-week computerized system | Missing check forms dropped from 2% to 0%; video, interviews, and surveys indicated improved compliance, productivity, and worker satisfaction. | Digital recording can outperform paper when embedded in task flow and linked to immediate operational value (Goomas & Yeow, 2013). |
| Warehouse scanners | Human-factors analysis of rugged handheld scanners | Scanners replaced pen-and-clipboard workflows, but existing form factors had yielded most available efficiency; line-of-sight concepts target non-value-added wrist motions. | Digital adoption depends on embodied ergonomics, not only data architecture (Nair et al., 2018). |
| Public employment services | 25 interviews and more than 80 hours of observations | Workers used automatic, extended, and in situ preparation to make automated client representations usable. | Digital and automated records require interpretation, repair, and improvisation (Jørring, 2025). |
| Civil-service benefit disputes | Ethnographic study of concurrent Lotus NOTES and paper files | Paper carried perceived “meta-information” and helped defend professional practice and status. | Paper can function as a trust, craft, and authority device inside bureaucracy (Komito, 1998). |
Speed is not the same as digitization
The evidence sharply separates digitization from speed. In nursing, EHR implementations in Moore et al.’s (2020) review were associated with weighted documentation-time increases of +22% and +46%, yet barcode medication administration reduced medication-administration time by 33% (P < .05). These findings are not contradictory if speed is treated as task-specific rather than system-wide. A digital module that requires more screens, delayed access, or later transcription may slow documentation; a barcode medication system that fits the medication-administration task may reduce time (Moore et al., 2020; Fraczkowski et al., 2020).
Warehouse evidence reinforces this interpretation. Goomas and Yeow (2013) compared an eight-week paper baseline using pre-printed operator pre-shift inspection reports with a five-week computerized safety-check system integrated into the warehouse management system and barcode readers. The computerized system blocked work assignment until checks were completed and provided immediate feedback; missing check forms dropped from 2% to 0%, and video, interviews, and surveys indicated improved compliance, productivity, and worker satisfaction (Goomas & Yeow, 2013). Here the digital record did not ask workers to step away from the workflow in order to satisfy an external documentation requirement. It became part of getting the work assignment itself.
The practitioner lesson is not that warehouses are easier than hospitals or schools. The evidence does not justify that broad claim. The narrower, evidence-grounded point is that digital recordkeeping gains acceptance when it gives immediate operational value at the point of work. In the Goomas and Yeow (2013) case, the computerized system connected completion of safety checks to work assignment and feedback. In the clinical studies, by contrast, paper often supplied speed and visibility that the EHR did not provide at the needed moment (Flanagan et al., 2013; Stevenson et al., 2016).
Stress signals failures of trust and repairability
Trust in a digital record depends not only on whether data exist, but also on whether workers can retrieve, correct, and rely on them. AlQahtani et al. (2021) surveyed 212 nurses at a tertiary eye hospital in Saudi Arabia and found that 106 nurses—50% of respondents, with a 95% confidence interval of 43.3–56.7—reported EHR-related stress; 35 nurses, or 16%, reported severe EHR-related stress. The leading stressors were incomplete EHR work by other departments affecting nursing care (70.8%), difficulty correcting data after entry (60.4%), and difficulty retrieving data (60.4%) (AlQahtani et al., 2021). Those stressors point directly to repairability and interdependence.
Analog fallback is understandable under those conditions. If another department’s incomplete entry can affect nursing care, if an error is difficult to correct after entry, and if retrieval is difficult, then a local paper note may feel safer for immediate action. That inference is the author’s reasoning from AlQahtani et al.’s (2021) reported stressors; the study itself does not measure paper fallback as the outcome. The reasoning is consistent, however, with studies that document paper notes and charts as workflow supports in clinical settings (Flanagan et al., 2013; Fraczkowski et al., 2020; Stevenson et al., 2016).
Trust also has an interpretive dimension. Komito (1998) found that paper files in a civil-service benefit-dispute office carried perceived “meta-information” essential to work and supported workers’ defense of professional practice. Jørring (2025) similarly shows that automated client representations in employment services do not simply deliver usable knowledge; frontline workers must simplify, extend, or improvise around them through digital coping strategies. Together, these studies show that the official record may be distrusted not because workers reject accountability, but because they know the record does not contain everything needed for situated judgment.
Hidden labor is the price of parallel systems
Paper’s return becomes organizationally costly when it creates parallel systems. Moore et al. (2020) report that nurses often documented informally on paper before entering the same information electronically, producing duplication and potential transcription-error risk. Grant (2024) documents a school version of the same phenomenon at institutional scale: at least two commercial platforms coexisted with a bespoke pupil performance and intervention system, six yearly data drops, spreadsheets, phone calls, handwritten notes, printed documents, and a full-time administrator handling data entry, data cleaning, handwritten-data input, cross-platform transfer and translation, reporting, and printing.
The hidden workload is not merely clerical inconvenience. In special education, the U.S. Government Accountability Office (2016) found that educators in focus groups commonly estimated spending roughly one to two hours per day on administrative tasks and worried this took time from the classroom. The report also found that federal efforts to reduce IDEA paperwork, including multi-year IEP pilots, paperwork waivers, and model forms, were used sparingly; no state applied for the pilots, with states citing limited perceived benefit and inadequate funding to implement and evaluate them (U.S. Government Accountability Office, 2016). At the same time, stakeholders acknowledged that IDEA documentation serves accountability, planning, and student-support functions (U.S. Government Accountability Office, 2016). The burden is therefore not solved by declaring documentation unnecessary. It is produced by the interaction between legitimate accountability functions and the labor required to satisfy them.
Grant’s (2024) school ethnography helps explain why digital systems can intensify this interaction. When data platforms require inputs from teachers, parents, administrators, and external systems, someone must chase late entries, account for missing data, translate across platforms, and circulate reports. The work may be invisible to those who see only dashboards or final reports. This evidence supports the article’s claim that paper’s quiet return is often a symptom of hidden infrastructural labor rather than a residual preference for older forms.
Mechanisms: Trust, Speed, Error, and Visibility
The cross-sector evidence supports four mechanisms through which paper becomes preferable or persistent. These mechanisms are analytical categories proposed here; they are not a claim that every workplace uses paper for all four reasons. A given paper form may serve one function while creating risks in another.
Mechanism 1: Paper is immediately available when the digital system is not
Immediate availability includes physical access, cognitive simplicity, and temporal fit. In Flanagan et al.’s (2013) EHR study, paper was useful for memory and efficiency. In Stevenson et al.’s (2016) vital-sign study, handwritten notes and pre-printed observation charts smoothed workflow. Fraczkowski et al. (2020) identify insufficient time, environmental constraints, barcode and ID accessibility problems, and usability issues such as multiple screens as causes of nurses’ EHR workarounds. These findings converge on a simple point: a recordkeeping medium that is technically available but slow to access at the point of care is not fully available in practice.
In warehouses, the same mechanism appears in a different form. Nair et al. (2018) note that rugged handheld scanners, also called rugged mobile computers, are used in receiving, order picking, and put-away and were introduced to replace pen-and-clipboard workflows. Their human-factors argument is that scanner form factors had not fundamentally changed since that replacement and that warehouses had extracted most available efficiency from existing rugged-scanner designs; the proposed line-of-sight scanner concept targets non-value-added wrist motions (Nair et al., 2018). The implication for paper persistence is that digital devices must be judged as embodied tools, not just as portals into a database. If a scanner or EHR terminal produces awkward movements, repeated interruptions, or extra navigation, workers may prefer a paper surface that better matches the body’s motion and the task’s rhythm.
Mechanism 2: Paper makes selected problems visible
Digital systems often promise comprehensive records, but comprehensive storage is not the same as practical visibility. Flanagan et al. (2013) report that paper helped make clinical problems visible. Stevenson et al. (2016) show that vital-sign documentation accuracy and completeness matter for recognizing patient deterioration, and that nurses used paper observation charts alongside electronic records. The article’s interpretation is that paper can function as a display technology: it can put selected cues into view in a way that supports rapid noticing. This is not a claim that paper is always more visible than a screen. It is a claim that visibility is designed, and paper sometimes supplies a better local design.
School data work also depends on visibility, though the object is institutional performance rather than patient status. Grant (2024) describes digital and physical displays, reports, software outputs, spreadsheets, handwritten notes, and printed documents as part of the school’s data infrastructuring. The coexistence of these artifacts suggests that no single platform supplied all the forms of visibility required for intervention, reporting, and coordination. The same logic appears in Jørring’s (2025) public-employment study: automated representations required preparation strategies because workers needed meaningful client understandings for meetings, not merely system-generated profiles.
Mechanism 3: Paper protects local judgment when official records are hard to repair
When workers fear that a digital entry is difficult to correct, paper can serve as a buffer. AlQahtani et al. (2021) report that 60.4% of surveyed nurses identified difficulty correcting data after entry as a leading EHR-related stressor, and another 60.4% identified difficulty retrieving data. Those percentages do not prove that nurses then used paper, but they do identify conditions under which analog notes would be a rational local safeguard. Komito’s (1998) civil-service study adds that paper may protect interpretive judgment and occupational status by preserving meta-information that workers perceive as missing from electronic files.
This mechanism has an ambivalent ethical status. On one hand, protecting judgment can mean preserving context that a standardized digital field cannot capture. Jørring’s (2025) workers repaired and supplemented automated client representations because official representations were not automatically meaningful. On the other hand, local paper buffers can reduce transparency if relevant information never enters the official record. The sources support both sides of this tension: paper supports professional practice and interpretation (Komito, 1998), but duplication and transcription into formal systems can create error risk (Moore et al., 2020).
Mechanism 4: Paper transfers work across time and roles
Paper’s convenience at one moment can create work later. A handwritten note taken during a rushed clinical episode may be fast for the nurse but require later transcription into the EHR; Moore et al. (2020) identify this informal paper-to-electronic pattern as duplication with transcription-error risk. A handwritten input from a teacher or parent may solve a participation problem in a school data process, but the data office must later enter, clean, and translate it; Grant (2024) documents exactly these kinds of school data tasks. A paper inspection form may be familiar to an equipment operator, but missing forms remained an issue in Goomas and Yeow’s (2013) paper baseline, whereas the computerized system reduced missing check forms from 2% to 0%.
This transfer mechanism is central for managers. The worker who prefers paper may be making a rational choice within a constrained task, while the organization accumulates hidden costs through delayed entry, reconciliation, and audit vulnerability. Conversely, a manager who bans paper may remove a safety-relevant cognitive aid without addressing why the official system is unusable at the point of action. The evidence supports neither blanket permission nor blanket prohibition.
Counterarguments: When Digital Records Deserve the Preference
The strongest counterargument to this article’s thesis is that paper persists because organizations tolerate noncompliance and because digital systems, when properly implemented, produce more complete, auditable, and timely records. This is not a weak argument. Several sources in the evidence base support it.
The compliance argument
Goomas and Yeow’s (2013) distribution-center case is the clearest example. The computerized equipment safety-check system was integrated into the warehouse management system and barcode readers, blocked work assignment until checks were completed, and provided immediate feedback. Missing check forms fell from 2% to 0%, and multiple evidence streams indicated improved compliance, productivity, and worker satisfaction (Goomas & Yeow, 2013). If the same organization had treated paper forms as a necessary cognitive aid, it might have preserved a less reliable process. The counterargument is therefore that paper can be a weak control mechanism, especially when completion must be verified before work proceeds.
Moore et al. (2020) provide a second digital-favorable finding: barcode medication administration reduced medication-administration time by 33% (P < .05). This result blocks any romantic account of analog work. Some digital systems save time and may redistribute nurses’ time toward direct care and communication, according to the review’s broader findings (Moore et al., 2020). In addition, paper-to-EHR double entry can raise transcription-error risk (Moore et al., 2020). A patient-safety perspective can therefore argue that paper is not merely a harmless supplement; it can be a pathway for delayed or erroneous official documentation.
The education evidence also supports the compliance argument. The U.S. Government Accountability Office (2016) reports that IDEA documentation serves accountability, planning, and student-support functions. If paper reduction were pursued without regard for those functions, students could lose protections and educators could lose planning information. The GAO also notes that technology and data clerks could reduce some administrative burdens, although they introduced costs (U.S. Government Accountability Office, 2016). The defensible counterclaim is that better digital infrastructure and staffing, not renewed reliance on paper, should be the goal.
Response: the question is not analog versus digital, but operational fit
The counterargument succeeds against a blanket pro-paper position. It does not defeat this article’s thesis because the thesis is conditional: workers prefer or preserve paper when digital systems fail practical tests of speed, trust, visibility, repairability, and ergonomic fit. When the digital system passes those tests, the evidence suggests that paper can lose its advantage. Goomas and Yeow’s (2013) computerized safety-check system succeeded precisely because it was embedded in the work assignment process and delivered immediate feedback. Moore et al.’s (2020) BCMA finding likewise shows that a well-fitted digital intervention can reduce time.
The compliance argument also underestimates the difference between prohibiting a workaround and learning from it. Flanagan et al. (2013) argue that it is unrealistic to expect EHRs to eliminate all paper-based cognitive aids and that workaround patterns should inform human-factors redesign rather than simply be prohibited. Fraczkowski et al. (2020) show that workarounds arise from organizational factors, environmental constraints, patient-specific barriers, insufficient time, barcode/ID accessibility problems, and usability issues. If those causes remain, enforcement may suppress visible workarounds while preserving the underlying mismatch.
A further limit of the counterargument is that official digital completeness can mask hidden labor. Grant’s (2024) school case shows that commercial data platforms may depend on manual data entry, cleaning, cross-platform transfer, and printed circulation. The dashboard may appear digital, but the production process remains hybrid. In public employment services, Jørring (2025) shows that automated client representations still require workers to make them usable through preparation and improvisation. Digital records deserve preference when they reduce rather than relocate work, and when they preserve rather than flatten situated knowledge needed for action.
Limits of the evidence
The evidence base is heterogeneous. It includes ethnographies, qualitative observations and interviews, integrative and systematic reviews, a survey, a government report, a case study, and a human-factors design article. These sources cannot be combined into a single effect size for “paper preference.” The clinical findings do not automatically generalize to schools; school data infrastructuring does not automatically generalize to warehouses; and a successful warehouse safety-check system does not prove that all digital systems can be made acceptable by integration alone. This article’s cross-sector argument is therefore a theoretical and practical synthesis, not a meta-analysis.
There are also uncertainties inside the cited findings. AlQahtani et al. (2021) identify EHR-related stress and its determinants in one tertiary eye hospital in Saudi Arabia, but the reported survey findings do not establish that stress caused paper fallback. Komito’s (1998) study is older and focused on Lotus NOTES in a specific Irish civil-service setting, though its concepts of meta-information, craft, and status remain relevant to contemporary digital recordkeeping. Goomas and Yeow’s (2013) case reports a drop in missing forms from 2% to 0%, but it examines one distribution-center implementation over an eight-week paper baseline and a five-week computerized period. Grant’s (2024) ethnography provides rich evidence from one secondary school rather than a sector-wide prevalence estimate.
These limits do not weaken the practical value of the synthesis; they define its proper use. Practitioners should not take the article as proof that their workers prefer paper for the same reasons documented elsewhere. They should use the framework to investigate local episodes of recordkeeping before deciding whether to redesign, formalize, replace, or prohibit analog records.
A Practitioner Protocol for Acting on Paper’s Return
The application question is not “How do we eliminate paper?” but “What work is paper doing, and what risk does that work create?” The evidence supports a four-part practitioner protocol: classify the function of paper, locate the hidden labor it creates, test whether digital alternatives are embedded in the task flow, and govern any remaining analog aids explicitly.
Step 1: Classify the paper artifact by function
Practitioners should begin by distinguishing at least five functions: memory aid, visibility aid, temporary capture tool, repair buffer, and unofficial duplicate record. This classification is author-generated, but it follows directly from the evidence. Paper served memory, efficiency, and visibility functions in integrated EHR environments (Flanagan et al., 2013). Handwritten notes and pre-printed observation charts supported workflow and patient safety in vital-sign documentation (Stevenson et al., 2016). Paper RN notes and handwritten notes later transcribed into the EHR appeared in nursing workaround studies (Fraczkowski et al., 2020). Paper files carried meta-information in civil-service work (Komito, 1998). Handwritten notes and printed documents supported school data infrastructuring (Grant, 2024).
The practical rule is to avoid moralizing the artifact before classifying it. A bedside jotting that prevents loss of information during immediate care is different from a parallel notebook that never enters the official record. A printed school report used to prompt intervention meetings is different from a hidden spreadsheet that becomes the real pupil record. A paper safety checklist with missing forms is different from a digital check that blocks work assignment until complete (Goomas & Yeow, 2013).
Step 2: Map double entry and delayed officialization
After classification, organizations should map where information crosses from paper to digital, from one platform to another, or from one role to another. Moore et al. (2020) identify informal paper documentation followed by electronic entry as duplication with transcription-error risk. Grant (2024) documents handwritten-data input, cross-platform transfer and translation, and report compilation as part of school data work. The U.S. Government Accountability Office (2016) reports that educators commonly estimated roughly one to two hours per day on administrative tasks in special education contexts, while also recognizing that documentation supports accountability, planning, and student support.
The mapping should identify who benefits from each analog capture and who pays for it later. A clinician may gain speed while a later transcription step creates risk. A teacher may use a handwritten note because platform entry is unavailable at the needed moment, while a data administrator later absorbs cleaning and translation work. A public-service worker may supplement an automated representation during a client meeting, while the official file remains less informative than the worker’s situated understanding (Jørring, 2025). These examples are not new empirical findings from this article; they are applications of the cited evidence to practitioner diagnosis.
Step 3: Redesign the digital system around operational value
Where paper persists because the digital system is slow, inaccessible, or unhelpful, redesign should focus on immediate operational value. The strongest evidence comes from Goomas and Yeow’s (2013) computerized warehouse safety checks: the system was integrated into work assignment, used barcode readers, blocked work assignment until checks were complete, provided immediate feedback, and reduced missing check forms from 2% to 0%. The lesson for other sectors is not to copy barcode checks mechanically. It is to ask what the equivalent operational value would be in the local setting.
In health care, this may mean reducing multi-screen burden, improving barcode and ID accessibility, and designing digital capture around the point of care, consistent with workaround causes identified by Fraczkowski et al. (2020). It may also mean accepting that some paper-based cognitive aids should inform redesign rather than be banned, as Flanagan et al. (2013) argue. In nursing documentation, any redesign should attend to time consequences because Moore et al. (2020) report EHR documentation-time increases in weighted averages alongside time savings for BCMA. In settings where correction and retrieval create stress, redesign should improve repairability and data retrieval; AlQahtani et al. (2021) report that difficulty correcting data and difficulty retrieving data were each identified by 60.4% of surveyed nurses as leading stressors.
In schools, redesign should not assume that buying another platform will reduce workload. Grant (2024) shows that at least two commercial data-management platforms coexisted with bespoke systems and extensive manual maintenance. A practitioner response should budget for data cleaning, cross-platform translation, report circulation, and administrative labor rather than treating these as accidental residues. The GAO’s (2016) finding that technology and data clerks could reduce some burdens but introduced costs is especially relevant here.
In warehouses, redesign must include ergonomics. Nair et al. (2018) argue that digital recordkeeping in warehouse work is shaped by scanner form factors and non-value-added wrist motions. A digital system that is formally integrated but physically awkward may still invite shortcuts. Embodied fit is therefore a design criterion, not a peripheral usability preference.
Step 4: Govern legitimate analog aids instead of pretending they do not exist
Some paper aids may remain justified even after redesign. Flanagan et al. (2013) caution that it is unrealistic to expect EHRs to eliminate all paper-based cognitive aids. Stevenson et al. (2016) show that nurses created paper workarounds to smooth workflow and support patient safety in vital-sign documentation. Komito (1998) shows that paper can carry meta-information workers regard as essential to professional practice. The governance task is to decide which analog aids are legitimate, how they enter the official record when necessary, and when they must be retired because they create unacceptable error or accountability risks.
| Observed paper use | Likely frontline function | Main risk | Preferred practitioner response | Relevant evidence |
|---|---|---|---|---|
| Brief note used during immediate clinical action | Memory, speed, temporary capture | Delayed entry or transcription error if later copied into EHR | Redesign point-of-care capture; define required time and method for official entry | Flanagan et al. (2013); Moore et al. (2020); Stevenson et al. (2016) |
| Pre-printed observation chart beside electronic record | Visibility and safety monitoring | Inconsistent official record if chart and EHR diverge | Study what the chart makes visible; reproduce that visibility digitally or govern chart-to-EHR transfer | Stevenson et al. (2016) |
| School spreadsheet or handwritten list outside commercial platform | Data cleaning, translation, local intervention tracking | Hidden administrative workload and unofficial “real” record | Map platform gaps; resource data administration; reduce cross-platform translation where possible | Grant (2024); U.S. Government Accountability Office (2016) |
| Paper file consulted despite electronic case system | Meta-information, professional judgment, status protection | Opaque decision basis and uneven access to tacit knowledge | Identify what meta-information is missing; create structured ways to preserve context without relying solely on private paper knowledge | Komito (1998); Jørring (2025) |
| Paper safety checklist before warehouse work | Compliance documentation | Missing forms and delayed feedback | Embed digital check into work assignment and feedback if task structure permits | Goomas & Yeow (2013) |
| Digital scanner workarounds or avoidance | Response to ergonomic burden | Reduced compliance or productivity despite digital architecture | Assess device form factor, scanning posture, and repetitive motions | Nair et al. (2018) |
Audit questions for managers, clinicians, educators, and case supervisors
The following audit questions operationalize the protocol without requiring a major research project. They are author-generated questions grounded in the cited evidence.
- Where is the first record made? If the first record is paper and the official record is digital, examine duplication and transcription risk, as Moore et al. (2020) warn in nursing documentation.
- What does paper make visible that the digital system hides? Paper made clinical problems visible in Flanagan et al.’s (2013) study, and pre-printed observation charts supported vital-sign workflow in Stevenson et al. (2016).
- What error is the worker trying to avoid? Difficulty correcting and retrieving EHR data were leading stressors in AlQahtani et al. (2021), and automated client profiles required repair and improvisation in Jørring (2025).
- Who performs the later cleanup? Grant (2024) shows that digital school systems can depend on full-time administrative labor for data entry, cleaning, translation, reporting, and printing.
- Does the digital record provide operational value immediately? In Goomas and Yeow’s (2013) warehouse case, the computerized check blocked work assignment until completion and provided immediate feedback.
- Does the device fit the body of the work? Nair et al. (2018) show that scanner design and non-value-added wrist motions are central to warehouse productivity and acceptance.
- Which documentation functions are non-negotiable? The GAO (2016) reports that special education documentation supports accountability, planning, and student support, even as educators experience administrative burden.
- What professional knowledge is being protected by paper? Komito (1998) shows that paper can preserve perceived meta-information and professional authority inside bureaucratic work.
The protocol requires managers to treat frontline paper neither as deviance nor as wisdom by default. A paper artifact should be redesigned away when it mainly duplicates entry, delays official documentation, or compensates for fixable digital friction. It should be formalized when it supplies a safety-relevant cognitive or visibility function that the digital system cannot yet reproduce. It should be challenged when it protects status by keeping essential information inaccessible to other legitimate users. It should be replaced when a digital system can be embedded into the task flow with immediate feedback and ergonomic fit, as in the strongest warehouse evidence (Goomas & Yeow, 2013; Nair et al., 2018).
Conclusion
Paper’s persistence after digitization is best understood neither as technological backwardness nor as an innocent habit. The article has argued a more conditional thesis: frontline workers preserve or recreate paper when official digital systems fail practical tests of speed at the point of action, trust and repairability, visibility of relevant cues, and ergonomic fit with embodied work. Across the evidence reviewed here, paper appears as frontline infrastructure: a temporary working surface, memory aid, display device, repair buffer, and sometimes a shadow record. That interpretation explains why paper can support safe and efficient action in one setting while creating duplication, delay, and error risk in another.
The evidence supports this thesis by showing recurring gaps between official records and workable records. In clinical settings, paper remained useful for memory, efficiency, visibility, workflow smoothing, and patient-safety work even inside mature EHR environments (Flanagan et al., 2013; Stevenson et al., 2016). Nursing workarounds were associated with time pressure, environmental constraints, barcode and ID accessibility problems, and usability barriers rather than simple refusal of electronic documentation (Fraczkowski et al., 2020). At the same time, informal paper documentation followed by EHR entry produced duplication and potential transcription-error risk, while EHR implementations increased documentation time in reported weighted averages and barcode medication administration reduced medication-administration time (Moore et al., 2020). The school, public-office, and warehouse cases sharpen the point: digitization can relocate hidden labor into data cleaning, cross-platform translation, and printed circulation (Grant, 2024), automated representations still require professional preparation and improvisation (Jørring, 2025), paper may preserve perceived meta-information and professional authority (Komito, 1998), and digital systems can outperform paper when they are embedded in the task flow and provide immediate operational value (Goomas & Yeow, 2013; Nair et al., 2018).
The practical contribution is therefore diagnostic rather than prescriptive in a narrow sense. The proposed case-study application protocol, the recordkeeping-episode unit of analysis, the double-entry exposure heuristic, and the decision matrix are author-generated tools for local inquiry; they are not findings from newly collected fieldwork. Their purpose is to help managers, clinicians, educators, warehouse supervisors, and public-service administrators ask what work paper is doing before deciding whether to redesign, formalize, replace, or prohibit it. A ban on paper may remove a safety-relevant cognitive aid without fixing the digital misfit that produced it. Uncritical tolerance of paper may entrench delayed official records, hidden administrative labor, opaque judgment, and transcription risk.
The article’s limits are substantial and should govern its use. The evidence base is heterogeneous: ethnographies, qualitative observations, reviews, a survey, a government report, a case study, and a human-factors design article cannot be collapsed into a single estimate of “paper preference.” The cited studies vary by sector, national setting, technology, task, and outcome. Several findings are setting-specific: EHR stress in one Saudi tertiary eye hospital does not prove paper fallback; one warehouse safety-check implementation does not establish universal digital superiority; one school ethnography does not estimate sector-wide prevalence; and an older civil-service study cannot be treated as a direct map of all contemporary platforms. The synthesis is therefore a practitioner framework grounded in reported evidence, not a meta-analysis or an executed comparative study.
The open problems follow directly from these limits. Future work should execute the proposed episode-level protocol across sites, compare which paper functions are safety-supporting and which are mainly duplicative, measure double-entry exposure and delayed officialization in practice, and examine how repairability, retrieval, visibility, and ergonomics shape trust in digital records. Researchers should also study how legitimate professional judgment can be preserved without allowing essential information to remain inaccessible in private paper systems. For practice, the next step is not a renewed campaign for paperlessness, but disciplined inquiry into the local conditions under which paper becomes necessary, risky, or obsolete.
References
Citation Verification Summary
AlQahtani, M., AlShaibani, W., AlAmri, E., Edward, D., & Khandekar, R. (2021). Electronic Health Record-Related Stress Among Nurses: Determinants and Solutions. Telemedicine and e-Health, 27(5). https://doi.org/10.1089/tmj.2020.0059
Flanagan, M. E., Saleem, J. J., Millitello, L. G., Russ, A. L., & Doebbeling, B. N. (2013). Paper- and computer-based workarounds to electronic health record use at three benchmark institutions. Journal of the American Medical Informatics Association, 20(e1), e59–e66. https://doi.org/10.1136/amiajnl-2012-000982
Fraczkowski, D., Matson, J., & Lopez, K. D. (2020). Nurse workarounds in the electronic health record: An integrative review. Journal of the American Medical Informatics Association, 27(7), 1149–1165. https://doi.org/10.1093/jamia/ocaa050
Goomas, D. T., & Yeow, P. H. P. (2013). IT-assisted equipment safety checks system to improve compliance: A case study at a distribution center. Safety Science, 60, 77–86. https://doi.org/10.1016/j.ssci.2013.07.002
Grant, L. (2024). Data infrastructuring in schools: New forms of professional edu-data expertise and agency. Research in Education, 120(1). https://doi.org/10.1177/00345237241257177
Jørring, L. (2025). Automatically Prepared? How Frontline Workers Cope in the Face of Automation. Social Policy & Administration, 59(5), 962–971. https://doi.org/10.1111/spol.13105
Komito, L. (1998). Paper “Work” and Electronic Files: Defending Professional Practice. Journal of Information Technology, 13(4), Article 3. https://doi.org/10.1177/026839629801300403
Moore, E. C., Tolley, C. L., Bates, D. W., & Slight, S. P. (2020). A systematic review of the impact of health information technology on nurses’ time. Journal of the American Medical Informatics Association, 27(5), 798–807. https://doi.org/10.1093/jamia/ocz231
Nair, C., Tsiopanos, K., Martin, R., & Marshall, G. (2018). Increasing Warehouse Productivity With an Ergonomic Handheld Scanner. Ergonomics in Design: The Quarterly of Human Factors Applications, 26(3), 23–31. https://doi.org/10.1177/1064804618757281
Stevenson, J. E., Israelsson, J., Petersson, G., Nilsson, G., & Bath, P. A. (2016). Vital sign documentation in electronic records: The development of workarounds. Health Informatics Journal. https://doi.org/10.1177/1460458216663024
(Note: the DOI cited in this reference (10.1177/1460458216663024) resolves to a different record; verification used bibliographic search instead)U.S. Government Accountability Office. (2016). Special Education: State and Local-Imposed Requirements Complicate Federal Efforts to Reduce Administrative Burden (GAO-16-25). https://www.gao.gov/products/gao-16-25
Reviews
How to Cite This Review
Replace bracketed placeholders with the reviewer’s name (or “Anonymous”) and the review date.